

CSF (Cerebrospinal Fluid) Leaks
Do you experience a headache that worsens when you stand up, and improves when you lay down? If so, you may be suffering from a low-pressure headache, or CSF leak headache (also known as low-pressure headache, intracranial hypotension, spinal headache). A CSF leak headache is one of the most common causes of a positional headache triggered by standing, and should always be considered in evaluations with your doctor.
CSF leaks can be debilitating. Classically, a CSF leak headache is a positional headache which goes away when lying down and becomes severe when standing up. Left undiagnosed, they can cause years of miserable chronic daily headache with a variety of other neurologic symptoms as we’ll discuss below. They often get misdiagnosed as chronic migraine, or other chronic daily headache disorders.
Understanding the causes of these headaches and evaluating for other sources of positional headache is crucial for proper diagnosis and treatment. This blog will discuss what a CSF leak is, who gets them, how they occur, what are CSF leak symptoms, the mimics of a CSF leak, how to test for a CSF leak, and CSF leak treatment strategies.
Positional Headache; Why Does My Head Hurt When I Stand Up?
Experiencing an orthostatic headache (headache that intensifies upon standing) can be perplexing and distressing. Postural headaches can suggest several different causes, one of which is a low-pressure headache, or CSF leak headache. The fundamental mechanics behind this type of headache are rooted in the dynamics of CSF within our central nervous system. Under normal circumstances, CSF fluid cushions, supports, cleanses and removes cellular debris from the brain and spinal cord, maintaining a harmonious balance of pressure inside and outside the brain and spinal cord tissues. There is approximately 150 mL around and in the brain and spinal cord in a normal adult. The choroid plexus tissues in the brain produce about 400-600 mL CSF every day, and the entire volume of CSF is replaced about 3-5 times per day.
However, when the pressure of the CSF drops from a CSF leak, the brain lacks its usual support, leading to a “sagging” effect when standing. This sagging increases the strain on pain-sensitive structures within the skull, such as nerves, blood vessels, and the thick dural membrane around the brain which attaches to the inside of the skull. The result of this sagging strain on these structures manifests as a headache. The unique characteristic of these headaches is their positional nature; lying down often brings relief by allowing the CSF pressure to normalize across the brain and spinal cord, reducing the tension on these sensitive structures.
Understanding the nuances of why your head hurts when you stand up is crucial in navigating towards an accurate diagnosis and effective treatment plan. The mechanics behind low-pressure headaches illustrate the delicate balance maintained within our bodies and how disruptions to this balance can significantly impact us. Recognizing the positional nature of these headaches as a key symptom can guide your doctor toward the root cause and the appropriate treatment.
What Is A CSF Leak?
Imagine a balloon in the shape of an elongated tube with a widening at the top into the shape of a ball. Now, imagine the inside of this entire balloon is filled with water, so it is very firm anywhere you push on it.
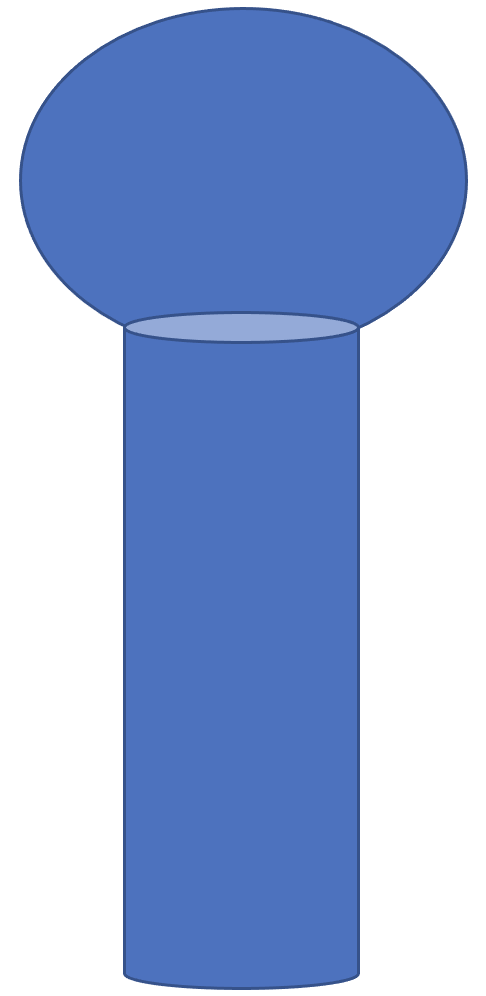
Then, imagine you take a pin and poke a hole in it and water starts to seep out. The pressure on the inside decreases due to the leak, and the ball appearing structure at the top begins to sag. This is the basic concept of what happens during a CSF leak.
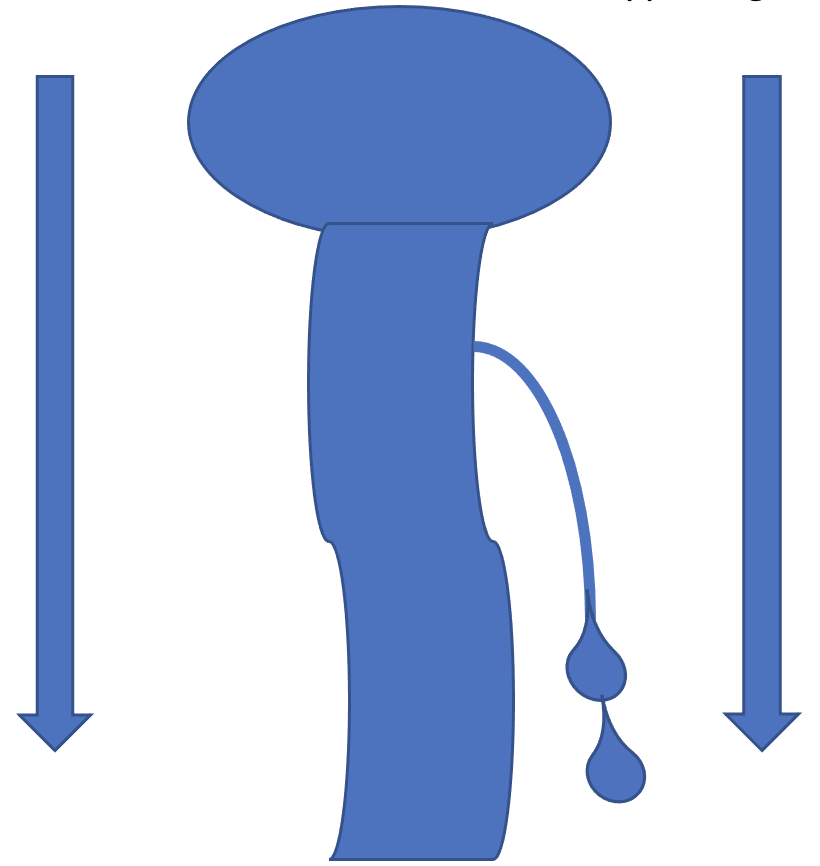
Now, imagine this water filled balloon is surrounded and protected by the vertebrae of the spinal column and the bones of the skull. However, the water represents the CSF. Inside the spinal canal and skull, the rubber balloon layer represents the membrane called the dura mater which keeps all the CSF in place and prevents it from leaking out. It is a continuous layer lining the inside of the spinal canal, continuing upwards along the inside of skull bones as well. This system keeps the CSF pressure within a certain normal range. The purpose of this CSF enclosed system is to cushion and keep the spinal cord and brain afloat, and to keep it clean of cellular debris. Similar to the balloon example above, if there is a small leak in this dura mater membrane somewhere along the spinal canal or along the base of the skull (such as through sinuses), CSF escapes. Intracranial pressure and intraspinal pressure within this system then decrease (and deflate, like a balloon). The result of the CSF leak is intracranial hypotension (low pressure) with subsequent sagging of the brain and spinal cord.
You now understand the concept of a CSF leak. That’s the easy part though. The difficulty is understanding why it developed, how to find and test for the specific location of the leak, and most importantly, how to seal the leak.
Types of CSF Leaks
The genesis of low-pressure headaches is as complex as it is varied, embedding itself in the intricate interplay of our body’s internal pressures and the resilience of its structures. Intracranial hypotension, the technical term for decreased pressure in the space surrounding the brain and spinal cord, underpins the main culprit of these symptoms. This condition can emerge from a myriad of sources.
The primary trigger is a breach in the dura mater, the thick fibrous membrane encasing the brain and spinal cord, leading to CSF leaks. This efflux of CSF results in a drop in the cranial and spinal pressures, giving rise to the characteristic headache that intensifies upon standing (orthostatic, or positional headache). Let’s review the two main types of CSF leak; spinal CSF leaks or cranial (skull) CSF leaks.
Spinal CSF Leak Causes:
These CSF leaks come from somewhere along the spinal column. There are a variety of tests used to locate a spinal leak, but we’ll discuss those later.
1) Iatrogenic (most common for spinal leaks):
Lumbar puncture (the leading cause of post-dural puncture headache), epidural injections or anesthesia (such as during childbirth), and spinal surgery. Risk is lower with experienced operators, smaller needles, and atraumatic (pencil-point) needles.
2) Traumatic:
Spinal injuries, falls, sports injuries, or occasionally chiropractic manipulation.
3) Spontaneous intracranial hypotension (SIH:
No clear major trauma or other initial clear reason. These usually just come on out of the blue. SIH can occur in anyone, but has a female predominance with a peak incidence around age 40. The annual incidence of SIH is estimated at ~5 per 100,000. The Schievink classification (based on a large series) includes:
- Type 1: Dural tears (~27%), mostly ventral (often associated with calcified discs, osteophytes, bone spurs).
- Type 2: Meningeal diverticula (~42%).
- Type 3: CSF-venous fistulas (increasingly recognized).
SIH can be associated with underlying dural membrane weakness, heritable connective tissue disorders (e.g., Ehlers-Danlos Syndrome, Marfan-like features). Occasionally intracranial hypertension (IIH; pseudotumor cerebri) can be a source of these types of CSF leaks (especially from the skull base and sinus areas). In these cases, when CSF pressure increases too high, the dural membrane can spring a CSF leak from the pressure. When it seals up, then the pressure builds back up again. Some patients can rarely fluctuate between IIH and CSF leaks, depending on the CSF pressure status.

Cranial (Skull) CSF Leak Causes:
These involve a defect in the skull base (most often anterior skull base) communicating with the nasal cavity, sinuses, or middle ear. These types of CSF leaks are often associated with watery CSF drainage from the nose (rhinorrhea) or from the ear (otorrhea). The fluid is often fairly excessive (more than simply the type of drainage from a normal runny nose) and often clear or slightly yellow in color.
1) Trauma (most common):
Closed or penetrating craniofacial injury causing skull base fracture is the most common cause of this type of CSF leak. Common sites include the cribriform plate, ethmoid, sphenoid, and frontal sinus. CSF leak complicates roughly 10–30% of basilar skull fractures and 1–3% of closed head injuries. Most present within 48 hours to 3 months; many close spontaneously.
2) Iatrogenic:
Endoscopic sinus surgery (especially ethmoid/cribriform), neurosurgical procedures (e.g., transsphenoidal, skull base surgery), and less commonly other ENT or cranial surgeries.
3) Spontaneous:
Often linked to elevated intracranial pressure (idiopathic intracranial hypertension/IIH), congenital skull base defects, or erosion by tumors. Risk factors include obesity, female sex, and obstructive sleep apnea.
Cranial CSF leaks can also provide an entry for bacteria or viruses into the CSF which can lead to meningitis, so it’s important to seal the leak as soon as possible. Ear nose and throat (ENT) doctors often evaluate these types of leaks. They have the patient collect fluid from the nose and it is tested for CSF by a beta-2 transferrin assay. ENT surgeons or neurosurgeons (depending on leak location) surgically repair these types of leaks.
One clinical aspect is that skull base leaks rarely produce the classic low CSF orthostatic positional headache syndrome in contrast to spinal CSF leaks (but still possible). When spontaneous, they are usually linked to elevated intracranial pressure (IIH) rather than low pressure with an orthostatic positional headache.
What Is Considered Low CSF Pressure (Intracranial Hypotension)?
According to ICHD3 criteria, intracranial hypotension (low CSF pressure) is considered less than (<)6 cm CSF (<6 cm H2O, <60 mm CSF, < 60 mm H2O) when opening pressure is checked on a lumbar puncture. An accurate reading when checking for low or high pressure requires the correct positioning, which is specifically in the lateral decubitus position (lying on your side), preferably with legs extended. CSF pressures checked while sitting are not valid for an accurate reading.
Normal CSF pressure is generally considered 10-25 cm CSF, but exact reference ranges may vary by position, BMI, study, and age. It’s important to note that studies have shown that 1/3rd up to 1/2 with confirmed spontaneous intracranial hypotension have normal opening pressures. So a normal CSF pressure doesn’t definitively exclude the potential for a CSF leak.
What Are The Symptoms of CSF Leak Headaches?
These headaches typically manifest as a dull, throbbing pain that significantly intensifies when standing up (orthostatic or positional headache), or dull tension headaches. They resolve or improve dramatically upon lying flat because the recumbent position helps to even out the distribution of cerebrospinal fluid. These distinguishing characteristics are a direct result of the shifting pressures and tension on the dural membrane within the skull and spinal column.
A large systematic review and meta-analysis of published studies revealed the following frequencies of CSF leak symptoms:
1) Headache (97%)
Headache is the most common symptom of a CSF leak and occurs in 97% of patients. However, 3% may NOT have any headache! Of those that do have a headache, 92% of them are the classic orthostatic headache (positional headache). This means that the headache comes on when you are standing and resolves when you are lying down. Typically within 15 minutes of standing the headache significantly intensifies. However, some chronic CSF leaks can also steadily increase through the day after being upright all day long and be worst in the evening. The other 8% of headaches are non-orthostatic headache (they may not have a positional/orthostatic character). The headache location for a CSF leak in order of frequency is most often occipital (33%), diffuse throughout the head (30%), frontal (21%), fronto-occipital (11%), or temporal (8%).
2) Nausea/vomiting (54%)
Nausea and vomiting are frequent, adding to the overall discomfort and indicating the severity of the pressure imbalance. These symptoms can make the headache appearance similar to an intractable migraine or chronic migraine. Many patients end up getting treated for chronic daily headache and chronic migraine for years if their physician doesn’t take a detailed history of symptoms, progression of headaches, and the proper type of imaging.
3) Neck pain and stiffness (43%)
Neck pain is a commonly associated symptom with many headache disorders, including a CSF leak. Headache pain in the back of the head and neck stiffness are common, often described as a “rigid” sensation that makes turning the head uncomfortable.
4) Other ear-related symptoms (33%)
May include ear fullness, hyperacusis (everything sounds very loud).
5) Hearing disturbances (28%)
May include muffled, echoed, or distorted hearing. Changes in hearing, including muffled sounds or a ringing in the ears, suggest the leak’s impact on the ear’s inner workings.
6) Dizziness (27%)
7) Tinnitus (ringing in ears) (20%)
8) Vertigo (17%)
9) Reduced level of consciousness (15%)
This may be excess drowsiness, sleepiness or even disorientation.
10) Other visual symptoms (14%)
May include blurred vision, nystagmus, visual loss.
11) Back pain (14%)
Cervical radiculopathies have also been reported, as have numbness and tingling in the face, back of the head, and upper arms.
12) Photophobia (sensitivity to light) (11%)
Light sensitivity can make everyday environments feel overwhelmingly bright, signaling the brain’s heightened response to stimuli due to the lowered CSF pressure.
13) Movement disorders (10%)
These can manifest as gait disorder, Parkinsonism, ataxia, dysarthria (slurred speech), tremor, bradykinesia (slowness of movements), poor balance, chorea.
14) Diplopia (double vision) (6%)
One-sided (unilateral) or both sides (bilateral) 6th cranial nerve palsy is most common if there is a cranial nerve palsy. A 3rd, 4th, or multiple cranial nerve palsies are less common. With that said, all of these findings are quite rare.
15) Cognitive symptoms (6%)
May include cognitive impairment, behavioral changes, memory, and/or slow thinking.
16) Metallic taste
Some patients notice a metallic taste in the mouth, which can be peculiar and disconcerting.
It’s crucial to be vigilant about these symptoms, particularly if they persist or escalate. Each sign provides valuable clues about the nature of the headache and the potential involvement of a CSF leak. Understanding and recognizing these symptoms not only aids in seeking timely medical attention but also supports a more accurate diagnosis and the initiation of a targeted treatment strategy with your healthcare provider.
Where Are The Most Common Locations Of CSF Leaks In The Spine?
A large systematic review and meta-analysis of published data revealed the following frequencies of location:
1) Thoracic spine (41%)
2) Cervicothoracic junction (25%) (spinal region where the cervical and thoracic spine connect)
3) Multiple locations (24%)
4) Cervical spine (14%)
5) Lumbar spine (12%)
What Else Can Cause a Positional Headache? CSF Leak Mimics
A physical and neurological examination plays a pivotal role in helping to exclude other potential mimics of a CSF leak presenting as a positional headache. Some of these possible mimics from a different type of underlying cause could include a brain tumor, sinus infection, meningitis, Chiari malformation, cervicogenic headaches, or occipital neuralgia.
How Do You Test for CSF Leak? What is the Best CSF Leak Test?
Diagnosing a low-pressure headache entails a meticulous approach that combines a comprehensive patient medical history with advanced diagnostic techniques. The initial step in this journey is a detailed conversation, where your doctor gathers information on the headache’s characteristics, triggers, and alleviating factors, especially the notable improvement when lying down and worsening when upright.
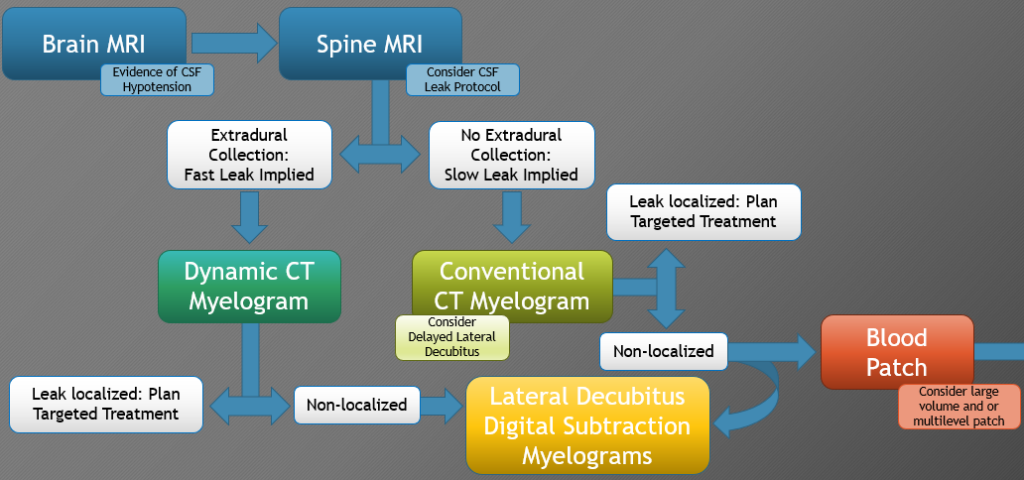
There isn’t necessarily a best CSF leak test, but there is a standard step-wise approach to testing, which typically begins with a contrast (with IV dye) brain MRI. There are a number of subsequent tests to provide further evidence of a CSF leak, and to localize the leak site. However, not all of these tests are universally available. Tests 1-5 below are considered the standard testing sequence. Tests 6-9 are not first line tests and many are not available in most institutions. The available options and protocols will vary between institutions depending on test availability and personnel to perform these diagnostic tests. I will discuss each of those test options below, and when each should be considered.
Here is an illustration of the CSF leak testing protocol sequence that some specialized academic medical institutions use:
1) Brain MRI With and Without Contrast
A CT scan of the brain is generally not a helpful test for looking for a CSF leak or for evaluation of spinal headaches. The best test to start with when a CSF leak is suspected is a brain MRI with contrast. This is the initial imaging test for a suspected CSF leak, sometimes complemented by MR venography (MRV) and MR angiography (MRA). The cornerstone of diagnosing low-pressure headaches and excluding more sinister mimics such as a brain tumor lies in the realm of imaging studies. Brain MRI with contrast has been shown to be the most sensitive in detecting signs of a CSF leak.
The contrast is really key with the brain MRI (unless medically contraindicated). The addition of IV contrast to the brain MRI is required to pick up the enhancement of the meninges caused by inflammation from the sagging of brain structures. This will not be seen without contrast, so it is important to discuss adding contrast with your doctor.
Unfortunately, brain MRI does not give any information about the location of the CSF leak in the spine. So, if there is evidence of intracranial hypotension from CSF leak on the brain MRI, it needs to then be followed up by spine imaging to locate the site of the CSF leak in order to seal it.
Brain MRI will often show some of the classic features of CSF leaks. The brain MRI findings occur because of the brain sagging down (recall the leak dynamics discussed above). Pachymeningeal enhancement and sagging of the brain structures are both hallmark indicators of reduced CSF pressure, but there are other findings that we also look for. The most common features of a CSF leak on a brain MRI are:
a) Diffuse pachymeningeal enhancement (73%)
Imagine the sagging brain pulling down on the dura mater membrane which is attached to the inner skull lining. This causes inflammation and irritation of this layer, and it usually will light up (enhance) with contrast on the MRI. The result is diffuse, smooth, non-nodular pachymeningeal enhancement, a widespread thickening and enhancement (bright white coloration) of the dura mater. Sometimes if the MRI is done too early after the CSF leak develops, it may not show this enhancement yet. The reason is because there hasn’t been enough time to allow the inflammatory process to develop.
b) Venous engorgement (57%)
As the brain sags downward, the venous channels are also pulled downwards. This enlarges the inside of the veins and thus more blood collects in them. Engorgement of the epidural venous plexus can also be seen, as well as the transverse sinus venous distension sign.
c) Brain sagging (43%)
Following a CSF leak, the spinal fluid pressure decreases. Without the CSF cushioning and keeping the brain and spinal cord afloat, gravity has its way and pulls the brain downwards. Thus, you get the sagging brain. Signs of this on an MRI can be seen in a variety of often subtle ways including flattening of the ventral pons, descent of the cerebellar tonsils (pseudo-Chiari), partial effacement of basal cisterns, inferior displacement/flattening of the optic chiasm, reduced mamillopontine distance, thinning of suprasellar cistern, obliteration of prepontine cistern, and decreased ventricular size. One publication showed that the likelihood of a CSF leak was increased with the following findings: effacement of the suprasellar cistern of 4 mm or less, effacement of the prepontine cistern of 5 mm or less, and mamillopontine distance of 6.5 mm or less. The image below is from a patient of mine with obvious brain sagging. I’ve drawn in these measurements as an example, which you can see show low CSF pressure leading to brain sag.
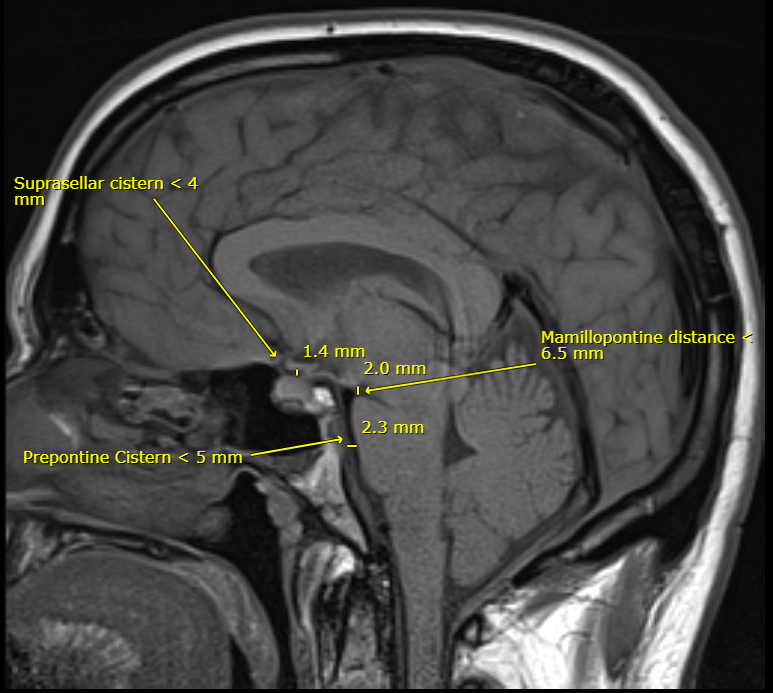
d) Pituitary gland enlargement/hyperemia (38%)
Without the normal CSF pressure pushing the pituitary gland down within its sella (the “cave” where the pituitary sits), the pituitary tissue is able to expand upwards when the CSF pressure is low. This can cause it to appear more plump or full.
e) Subdural collections (subdural hygromas) (35%)
These are fluid collections between the dura mater lining inside the skull and the arachnoid layer covering the brain. This fluid is made up of a variable mix of CSF, protein, and sometimes blood from tearing of the stretched little veins traveling between these membranes due to the downward traction. I’ve seen patients with subdural hemorrhages large enough to require burr holes drilled into the skull to release the blood and fluid out.
f) Normal brain MRI (19%)
Some patients appear to have a perfectly normal brain MRI. Therefore, a normal brain MRI does not exclude the possibility of having intracranial hypotension. Diagnosis really comes down to putting together all the clinical symptoms along with test results. If there is a strong suspicion for a CSF leak based on symptoms, then further imaging may be pursued (as detailed below).
2) Spine MRI Without Contrast, With Heavily Weighted T2 Imaging (CSF Leak Protocol)
A full spine MRI with “CSF leak protocol” (heavily weighted T2 imaging) of the cervical, thoracic, and lumbar spine is usually the next step in identifying the location of the CSF leak and looking for fluid collection along the spine. There are two benefits of this spinal MRI compared to going straight to CT myelogram. First, you do not need to puncture the dura mater (and risk then actually creating a CSF leak when there may not even be one present). Second, it does not require IV contrast.
3) Conventional CT Myelogram
If there is still a strong suspicion for a CSF leak based on clinical symptoms, but the brain and spine MRIs did not show clear evidence or location of a leak, or if the patient can not get an MRI, a CT myelogram is the next step.
Of note, if the spine MRI does show a CSF collection outside of the spine, then a fast CSF leak is likely present, and a conventional CT myelogram may not be able to identify the exact leak site. In this scenario, it is usually higher yield to move directly to a dynamic CT myelogram, or a digital subtraction myelogram (DSM), because these will be better at finding the exact leak site in a fast CSF leak. These two tests are described in more detail below.
CT myelography is done by doing a lumbar puncture and injecting CT contrast into the CSF under fluoroscopy. Then, the patient is taken to the CT scanner to obtain CT images of the spine to look for the specific location of the CSF leak along the spine.
This has often been an effective test for showing the precise location of the leak. However, it is more useful in slow leaks as opposed to fast leaks from large dural tears or multiple leaks. With fast CSF leaks, the injected contrast material spreads over multiple spinal levels before the CT can be completed, and this makes the exact leak site difficult to visualize. Digital subtraction myelography (DSM) or dynamic CT myelography are more useful for localizing fast leaks.
The downside of CT myelography (or any myelography) is that it requires a lumbar puncture, which then poses the risk of developing a CSF leak. So, if there isn’t actually a current leak, there’s a chance that one could develop from the procedure, although this isn’t common.
If the CSF leak is seen on the CT myelogram, further testing is usually not necessary. However, if it is still not seen or visualized well, more specialized testing may be required, and those options are discussed below.
4) Lateral Decubitus Digital Subtraction Myelogram (DSM)
If the spine MRI does NOT show a CSF collection outside of the spine, and/or a conventional CT myelogram does NOT identify a leak site (or a CSF-venous fistula could be present but not visualized), a lateral decubitus DSM is often the next best step.
If the spine MRI DOES show a CSF collection outside of the spine, a fast CSF leak is likely present. In that case, either a DSM or dynamic CT myelogram should be considered over a conventional CT myelogram since these will be more likely to visualize the exact leak location. If there is an extradural CSF leak on MRI, then a prone DSM is usually done first. If this is negative, then a lateral decubitus DSM is the next step.
A DSM is basically a CT myelogram under fluoroscopy while digitally subtracting pre-contrast images which then enhances the contrast visibility. It is very helpful in visualizing CSF-venous fistulas which often do not show up on other MR or CT spinal imaging, especially when done in the lateral decubitus (lying on your side) position. Lateral decubitus DSM is helpful in cases of CSF-venous fistula as well as nerve root sleeve tears, or a herniated disk or osteophyte (bone spur) tear in the dura mater layer.
DSM requires breath holding or is done under general anesthesia to stop breathing for a short time to prevent movement artifact. A limited number of published cases have shown a very high sensitivity (100%) for identifying the exact CSF leak site.
It has been suggested that DSM is particularly useful in localizing three types of CSF spinal leaks:
- Rapid leaks which can be seen on MR or CT myelography as extensive longitudinal extradural CSF collections.
- CSF leaks in front of (ventral) the spinal cord.
- CSF-venous fistulas between the spinal epidural veins and the subarachnoid space that are not visualized on MR or CT myelography. In one study, CSF-venous fistulas were found in 1/5th of patients with refractory intracranial hypotension with no identifiable CSF leak on spinal imaging.
5) Dynamic CT Myelogram (Hyperdynamic CT Myelogram)
If the spine MRI DOES show a CSF collection outside of the spine, there is a high probability of a fast leak. In that case, going straight to a dynamic CT myelogram (or a DSM) rather than a conventional CT myelogram is suggested because it will likely be higher yield in identifying the exact CSF leak site.
A dynamic CT myelogram is basically the same as a CT myelogram, but the timing of the procedure is different. Like a CT myelogram, CT contrast is injected into the CSF. However, the CT imaging is done simultaneously with the contrast injection into the CSF rather than a delay between contrast CSF injection and the CT images being taken.
Dynamic CT myelography is done in the lateral decubitus (laying on your side) and/or the prone (on your stomach) position. Some institutions do both sides of the spine on separate days to avoid excess contrast dye load.
Dynamic CT myelogram is often very useful in finding the exact location of a CSF leak, especially in fast leaks from a herniated disc or tear in the dura mater from an osteophyte.
6) MR Myelogram
This is the same concept as a CT myelogram except that it is done with an MRI and gadolinium (MRI contrast) is injected into the CSF by a lumbar puncture instead of CT contrast. It has excellent contrast resolution and there is no radiation exposure involved. However, intrathecal gadolinium is an off-label use. MR myelography can also be performed without gadolinium injected into the CSF (intrathecal injection), but the diagnostic yield may be better with contrast. This is not a commonly performed test.
The unconventional use of intrathecal gadolinium (injected into the CSF) is not commonly available. A limited number of published cases have shown a high sensitivity (75.5%) for identifying the exact CSF leak site. MR myelogram can be particularly helpful in looking for slow CSF leaks. However, intrathecal gadolinium has also been reported to cause neurotoxicity at higher doses. Furthermore, more recent studies have suggested that it may not be better overall compared to MR myelography without intrathecal gadolinium and there is some debate about this.
7) Radionuclide Cisternography (Radioisotope Cisternogram)
This test is a type of nuclear medicine imaging. It is performed by injection of a radionuclide tracer material by lumbar puncture into the CSF. Then images of the brain and spine are taken at certain intervals up to 24-72 hours to watch for the movement of the nuclear tracer.
A cisternogram assesses for abnormal CSF flow and is quite sensitive for detecting if there is a spinal CSF leak. However, it doesn’t provide information about the specific location of the leak. Therefore, it is not done as commonly as it had been in the past for a couple reasons. First, it does require a lumbar puncture which introduces the risk of a CSF leak if not already there. Second, if there is evidence of a CSF leak, it doesn’t help in localizing where it is in the spine. Therefore, if a lumbar puncture is being performed, it’s better to get more “bang for your buck” with a test such as a CT myelogram which will be more likely to show the location of the CSF leak so it can then be treated more precisely. Cisternograms are done much less commonly nowadays since we now have much better imaging options available, as discussed above.
8) MR Cisternography
This is also not a common test and is sometimes a consideration for evaluating suspected CSF fistulas along the skull base.
9) Spinal Tap (Lumbar Puncture; LP)
In instances where imaging alone does not provide definitive answers, or when the clinical suspicion for a CSF leak remains high, in the past a lumbar puncture would sometimes be performed to directly check the pressure. The lumbar puncture involves insertion of a thin needle in the lower lumbar spine and through the dural membrane to check the “opening pressure”. Of course, this seems contradictory because if there isn’t a CSF leak already, one could potentially form as a result of the procedure.
An LP alone is not routinely done anymore to check opening pressure for the sole purpose to determine the presence of intracranial hypotension from a suspected CSF leak. If an LP is done and the dura is going to be pierced, it just makes sense to combine it with one of the above diagnostic tests such as a CT myelogram. If an LP is done to check opening pressure, it should be done in the lateral decubitus position (lying on your side) for an accurate reading. This is equally important when evaluations for elevated CSF pressure from idiopathic intracranial hypertension (IIH) are being evaluated for.
Notably, a study showed that opening pressures in CSF leaks are not always low. In CSF leaks, opening pressure was found to be low (less than 6 cm CSF) in 67%, normal in 32% (6-20 cm CSF), and high normal (greater than 20 cm CSF) in 3% (highest noted was 22.8 cm CSF). Technically, the ICHD3 criteria for high CSF pressure is greater than 25 cm CSF. Regardless, the point is that the opening pressure result alone is not a definitive test of whether a CSF leak exists or not. Therefore, doing an LP simply for trying to diagnose low CSF pressure is not generally recommended because any benefit is outweighed by potential risk for developing a post-LP CSF leak.
CSF Leak Treatment
What are the treatments and medical procedures to fix a CSF leak? This can be a complicated question, depending on the source and type of leak. There is a general step wise progression of treatment options, depending on the response of each sequential treatment. It’s essential to navigate these treatment options under the guidance of a doctor experienced in managing low-pressure headaches.
1) Conservative Management
The first line treatment for a CSF leak is conservative treatment, non-invasive measures aimed at alleviating symptoms and restoring quality of life. This is effective in 28% of patients, without the need for any other treatments. Conservative treatments include bed rest, lying on your back (supine) as much as possible for 12-24 hours, hydration, pain medications, caffeine, steroids, and avoiding strenuous activity or exertional maneuvers.
Hydration is encouraged to increase blood volume, potentially offsetting the loss of CSF volume, while caffeine is sometimes recommended due to its ability to constrict blood vessels and increase cerebrospinal fluid pressure, providing symptomatic relief.
For those experiencing mild to moderate discomfort, over-the-counter pain medications may offer temporary respite. However, it’s crucial to use these judiciously, as over-reliance on pain relief medication can lead to rebound headaches, further complicating the treatment landscape, particularly if the patient also has migraines. Bed rest for several days can also aid in symptom management by promoting a natural balance in CSF pressure gradients, and natural sealing of the CSF leak.
2) Epidural Blood Patch
If conservative treatments fail, then an epidural blood patch is often the next step. What is a blood patch? This is an easy quick treatment in which some of your own blood is first collected. Many institutions combine fibrin glue to the blood in hopes of a stronger seal. That blood is then injected within the spinal canal (the epidural space, outside of the dura mater membrane) in the region where the CSF leak is suspected. Sometimes it is injected with fluoroscopic XR guidance, and other times without it. The theory is that as the blood clots, it will seal up the leak and facilitate normal pressure restoration, offering significant relief.
The first epidural blood patch is successful 64% of the time. Sometimes it may require 2 or 3 attempts, although for many the first treatment works. Large epidural blood patches (more than 20 mL) had better success rates at 77% compared to small epidural blood patches (less than 20 mL) at 66%.
Targeted (blood patch done at a precise spinal level) and nontargeted (blood patch done at a more regional area of the spine) blood patch techniques have shown similar successful results. Targeted blood patches were successful 70% of the time, while nontargeted blood patches were successful 69% of the time.
3) Surgical Repair of Dural Defects, Meningeal Diverticula, or CSF-Venous Fistulas
It is uncommon that these types of treatments are needed. However, if the above treatments are not successful, and the type of CSF leak is appropriate for surgery, these may be considered. In cases where a specific site of CSF leakage is identified, targeted therapies, including surgical repair, CSF venous fistula repair or focused epidural blood patch placement with interventional radiology, are pursued. Surgery may include suturing or packing the tear, ligating or clipping of nerve roots, or paraspinal vein embolization. These interventions require a high degree of precision and are typically recommended after careful consideration and detailed imaging studies.
4) Physical Therapy
Physical therapy is another component of a comprehensive treatment plan, especially for patients with predisposing factors such as connective tissue disorders. Strengthening the musculature that supports the spinal column can mitigate the risk of future leaks and contribute to overall well-being.
What Are The Complications Of A CSF Leak Repair?
Complications with a CSF leak repair are uncommon. Potential complications could include accidental dural puncture with blood injected into the CSF, arachnoiditis, nerve root compression, compression of the thecal sac (the “tube” structure described at the beginning which encloses the CSF), infection, or attempting to inject the blood patch into an area where there is no space for the blood patch to go (such as bad arthritis, prior spine surgery, scarring).
What Is Rebound Intracranial Hypertension After Treatment Of CSF Leak?
Rebound intracranial hypertension occurs when the CSF pressure starts to get too high after the CSF leak has been sealed. It has been reported to occur between 7%-27% of patients and begins within 24-48 hours of CSF leak repair.
This headache is usually worse in the morning or when lying down. The location of the pain often migrates from the back of the head to the face, like a mask. This uncommon event is more likely in younger women who are obese or those with a fast CSF leak with extradural CSF noted on the prior spine MRI. Rebound intracranial hypertension does not appear to be associated with blood patch level, blood patch volume, or opening pressure.
Rebound intracranial hypertension is usually mild and most often resolves on its own. When treatment is needed, options include acetazolamide, topiramate, methazolamide, furosemide, hydrochlorothiazide, spironolactone, triamterene, and ethacrynic acid. Rarely it can lead to papilledema requiring more aggressive treatments such as repeat lumbar punctures, lumbar drain for 5 days, stents or VP shunting.
When To See The Doctor For Your Headache
Navigating through the complexities of headaches, especially those that worsen when you transition from lying down to standing, necessitates a discerning approach and professional medical intervention. Low-pressure headaches from a CSF leak require a level of diagnostic precision and therapeutic insight that only a seasoned medical specialist such as a headache specialist or neurologist can provide.
It is essential to monitor the nature of your headaches, their frequency, intensity, triggers, and any new symptoms that you’ve noticed. A headache diary can be a valuable tool in this endeavor, capturing details that might illuminate patterns or precipitating factors. This information becomes a crucial component of your consultation, enabling a more targeted and efficient diagnostic and treatment process.
There is an added layer of urgency when symptoms persist or escalate despite initial conservative measures, or if they are accompanied by other concerning red flags such as nausea, stiff neck, fevers, or any new neurological features such as numbness, weakness, visual or speech disturbances, vertigo, or imbalance. These could be indicative of other secondary headache causes that demand immediate attention.
Conclusions
A CSF leak can be a debilitating and often missed and frustrating diagnosis. The abrupt onset of a positional headache which worsens when standing and improves when lying down is the most classic presentation. There are a variety of other neurological symptoms which can also occur with a CSF leak. If a CSF leak is suspected, it is important to get the proper testing done to confirm evidence and localization of the leak. Once the source of the leak is identified, sealing the leak often gives rapid improvement in symptoms, and the headaches will usually quickly resolve.
IF YOU HAVE HEADACHE, MIGRAINE, OR FACIAL PAIN AND ARE LOOKING FOR ANSWERS ON ANYTHING RELATED TO IT, A HEADACHE SPECIALIST IS HERE TO HELP, FOR FREE!
FIRST, LET’S DECIDE WHERE TO START:
IF YOU HAVE AN EXISTING HEADACHE, MIGRAINE, OR FACIAL PAIN DIAGNOSIS AND ARE LOOKING FOR THE LATEST INFORMATION, HOT TOPICS, AND TREATMENT TIPS, VISIT OUR FREE BLOG OF HOT TOPICS AND HEADACHE TIPS HERE. THIS IS WHERE I WRITE AND CONDENSE A BROAD VARIETY OF COMMON AND COMPLEX MIGRAINE AND HEADACHE RELATED TOPICS INTO THE IMPORTANT FACTS AND HIGHLIGHTS YOU NEED TO KNOW, ALONG WITH PROVIDING FIRST HAND CLINICAL EXPERIENCE FROM THE PERSPECTIVE OF A HEADACHE SPECIALIST.
IF YOU DON’T HAVE AN EXISTING HEADACHE, MIGRAINE, OR FACIAL PAIN DIAGNOSIS AND ARE LOOKING FOR POSSIBLE TYPES OF HEADACHES OR FACIAL PAINS BASED ON YOUR SYMPTOMS, USE THE FREE HEADACHE AND FACIAL PAIN SYMPTOM CHECKER TOOL DEVELOPED BY A HEADACHE SPECIALIST NEUROLOGIST HERE!
IF YOU HAVE AN EXISTING HEADACHE, MIGRAINE, OR FACIAL PAIN DIAGNOSIS AND ARE LOOKING FOR FURTHER EDUCATION AND SELF-RESEARCH ON YOUR DIAGNOSIS, VISIT OUR FREE EDUCATION CENTER HERE.
